
Breast Reconstruction Surgery: Types, Options and Recovery
On this page
What is Breast Reconstruction Surgery?
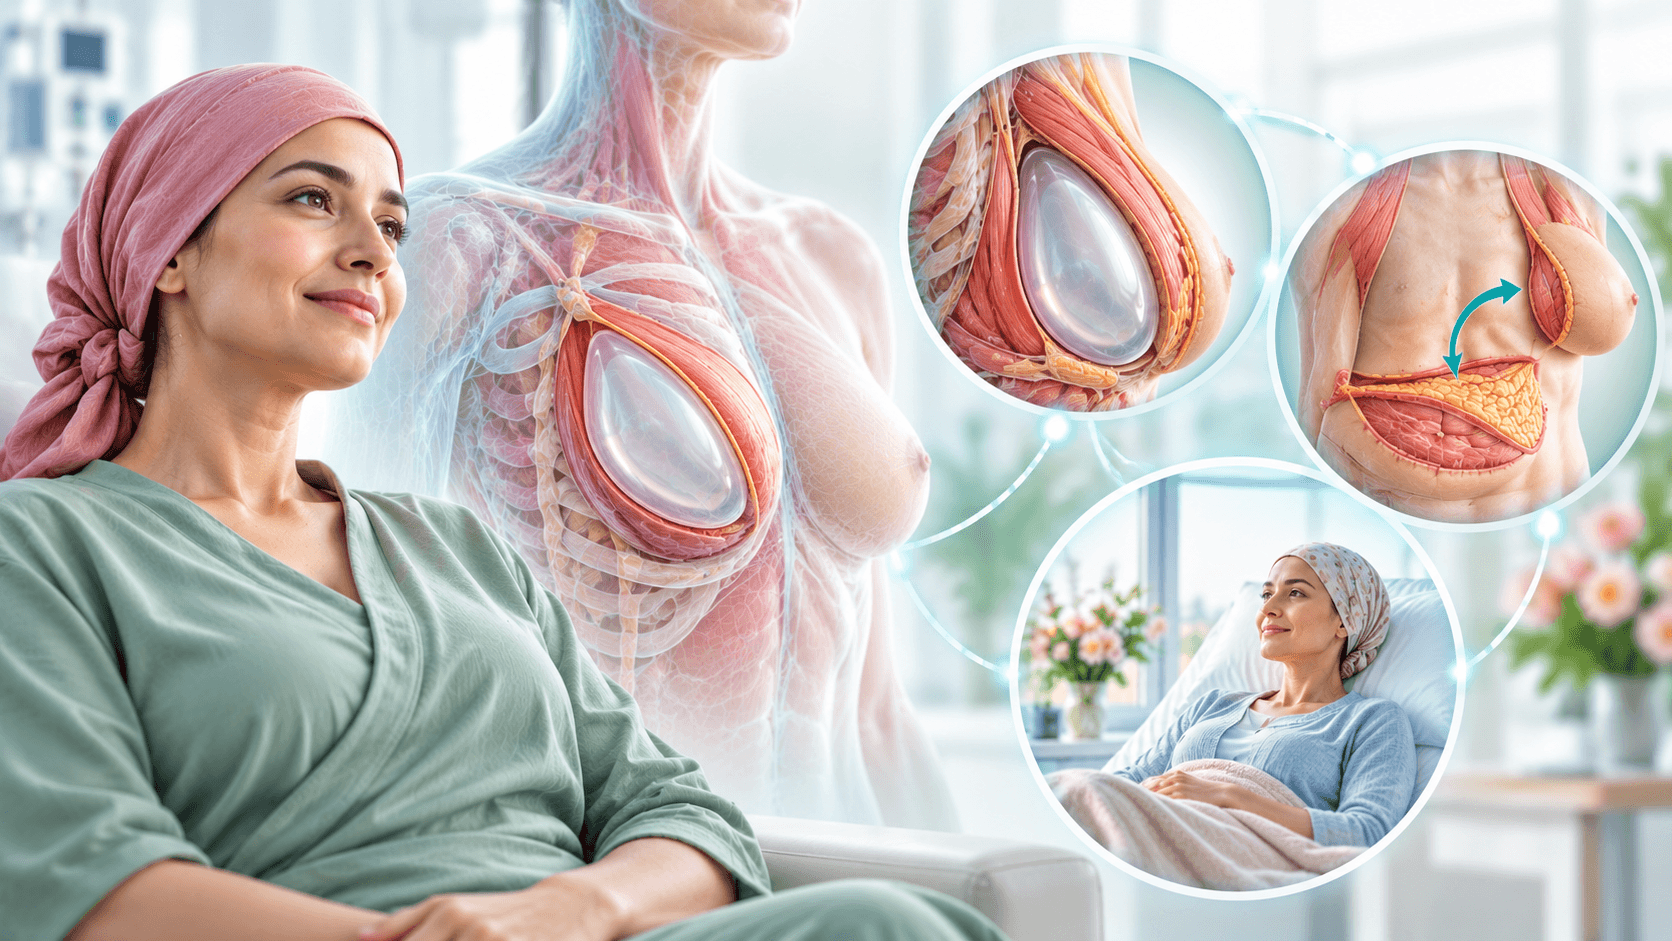
Breast reconstruction surgery is a procedure designed to restore the shape and appearance of the breast after part or all of it has been removed, usually because of cancer treatment or to lower cancer risk. It's most often done after a mastectomy (removal of the entire breast), but some patients who have had significant tissue removed during breast-conserving surgery may also consider it.
Types of timing:
- Immediate Reconstruction:Begins at the same time as the cancer surgery.
- Delayed Reconstruction:Performed months or years after the initial surgery, once healing is complete and other treatments are finished.
The best timing and reconstruction type depend on factors like your cancer stage, need for chemotherapy or radiation, health status, body type, and personal preferences, all of which are discussed with your medical and surgical team.
When is Breast Reconstruction Considered?
Breast reconstruction is an option if:
- You’ve had or are planning a mastectomy for invasive breast cancer, DCIS, or carry a high-risk gene mutation (like BRCA). There’s a major change in breast shape or symmetry after partial breast removal. You’re choosing risk-reducing mastectomy due to family history or genetics.
How Do Cancer Treatments Affect Reconstruction?
- Chemotherapy:If chemotherapy is needed, reconstruction can still start immediately, but certain steps may be timed around chemo cycles.
- Radiation Therapy:Radiation can affect skin healing and implant outcomes. Delayed reconstruction or specific techniques may be recommended if radiation is likely.
- Pathology & Staging:Sometimes final tumor details aren’t known until after surgery. In these cases, reconstruction may be delayed or staged to accommodate further therapy.
Close coordination between your surgical, oncology, and reconstructive teams is essential for the best outcomes.
Types of Breast Reconstruction
There are two main approaches:
- Implant-Based Reconstruction: Involves placing a silicone or saline implant to form the breast mound. Sometimes a tissue expander is used first, followed by a permanent implant once the skin has stretched.
- Direct-to-implant: In selected cases, a permanent implant is placed immediately.
- Flap (Autologous) Reconstruction: Uses your own tissue (skin, fat, sometimes muscle) from areas like the abdomen, back, thighs, or buttocks to create a new breast mound. Options include:
- TRAM Flap: Uses tissue and muscle from the lower abdomen.
- DIEP Flap: Takes skin and fat from the abdomen but spares the muscle.
- Other flaps use tissue from different donor sites.
Each method has its own benefits, risks, and recovery times.
Immediate vs. Delayed Reconstruction
| Aspect | Immediate Reconstruction | Delayed Reconstruction |
|---|---|---|
| Timing | Done during same surgery as mastectomy | Done months/years later, after healing/treatments |
| Number of surgeries | May reduce total surgeries | Often requires more procedures |
| Skin/nipple preservation | Better chance to save skin/nipple | More scarring; nipple usually reconstructed later |
| Emotional impact | Maintains breast shape right away | Period without breast mound, may affect body image |
| Flexibility | Less time to plan based on final pathology | Allows for decisions based on full treatment picture |
| Recovery | Longer initial surgery/recovery | Initial recovery is simpler; reconstruction later |
- Radiation therapy or complex cancer cases may benefit from delayed reconstruction for better outcomes and flexibility.

How is the Surgery Performed?
- Planning includes reviewing your health, treatment needs, and goals.
- Surgery is done under general anesthesia. For immediate reconstruction, plastic and breast surgeons may operate together.
- Implants or tissue flaps are used to create the breast mound.
- Nipple-areola reconstruction and symmetry adjustments may be done later.
- Recovery and the number of surgeries depend on the chosen technique and your treatment plan.
Recovery
- Implant-based:1–2 days in the hospital, quicker recovery, but may need several procedures.
- Flap-based:3–5 days in the hospital, longer recovery, with more restrictions due to the donor site.
- Pain is managed with medication, and activity is limited for several weeks.
- Drains may be used for 1–3 weeks.
- Multiple follow-ups are needed to monitor healing and plan next steps.
Risks and Possible Complications
- All surgeries carry risks such as:Infection Bleeding or hematoma Poor wound healing Blood clots
- Specific to implants: Capsular contracture (scar tissue tightening) Implant rupture or leakage Asymmetry or shifting Changes in sensation Very rarely, immune-related cancers linked to textured implants
- Specific to flaps:Partial/total flap loss Fat necrosis Donor site issues (scarring, weakness, hernia)
Regular follow-ups help detect and manage these risks early.
Choosing the Right Option
Your reconstruction choice is personalized, considering:
- Cancer type and treatment plan
- Body shape and available tissue
- Medical history and prior surgeries
- Radiation history
- Preferences about surgery/recovery and cosmetic goals
- Your surgeon’s expertise and available techniques
A collaborative discussion with your team ensures the plan matches your needs and expectations.
Key Points Breast reconstruction restores breast shape after cancer surgery, improving body image and symmetry.
Common questions
Can it be done at the same time as a mastectomy?
Yes, immediate reconstruction is possible for many patients.
What are the main types?
Implant-based and flap (autologous) reconstruction.
How long is recovery?
Implants: 2–4 weeks for light activities; flaps: 6–8 weeks or longer.
Is it painful?
Some discomfort is normal but well managed with medication.
Can it be done after radiation?
Yes, but timing and technique may vary.